
Who are we walking
through the door?
Pick your seat. The whole story — the journey, the economics, the platform — tailors to it.
Pick your seat. The whole story — the journey, the economics, the platform — tailors to it.
This is Eleanor. Her knee has hurt for a year, and tonight she's about to enter Medicare's new front door for musculoskeletal care. Pick your seat — the story will follow you down.

ACCESS is Medicare's new ten-year model that pays for outcomes, not visits, in chronic musculoskeletal care. It funds the journey you're about to scroll — and pays the clinicians who share it.
No voicemail, no portal login, no missed referral. The AI front door takes Eleanor's story the moment she's ready to tell it.
Red flags first. Then psychosocial risk and care gaps. She's enrolled on the spot — eligible, and at $0 cost-share.
A clinical team, a home exercise program, a coach who checks in. Pain trends down, function trends up — measured, not assumed.
A Care Update lands in the portal — or straight in the EHR. Five minutes of review, one coordination act, one billed co-management claim.
Her knee needs a surgeon. She arrives prepared: trended PROMs, documented conservative care, prior-auth-ready. Every seat in the system won.
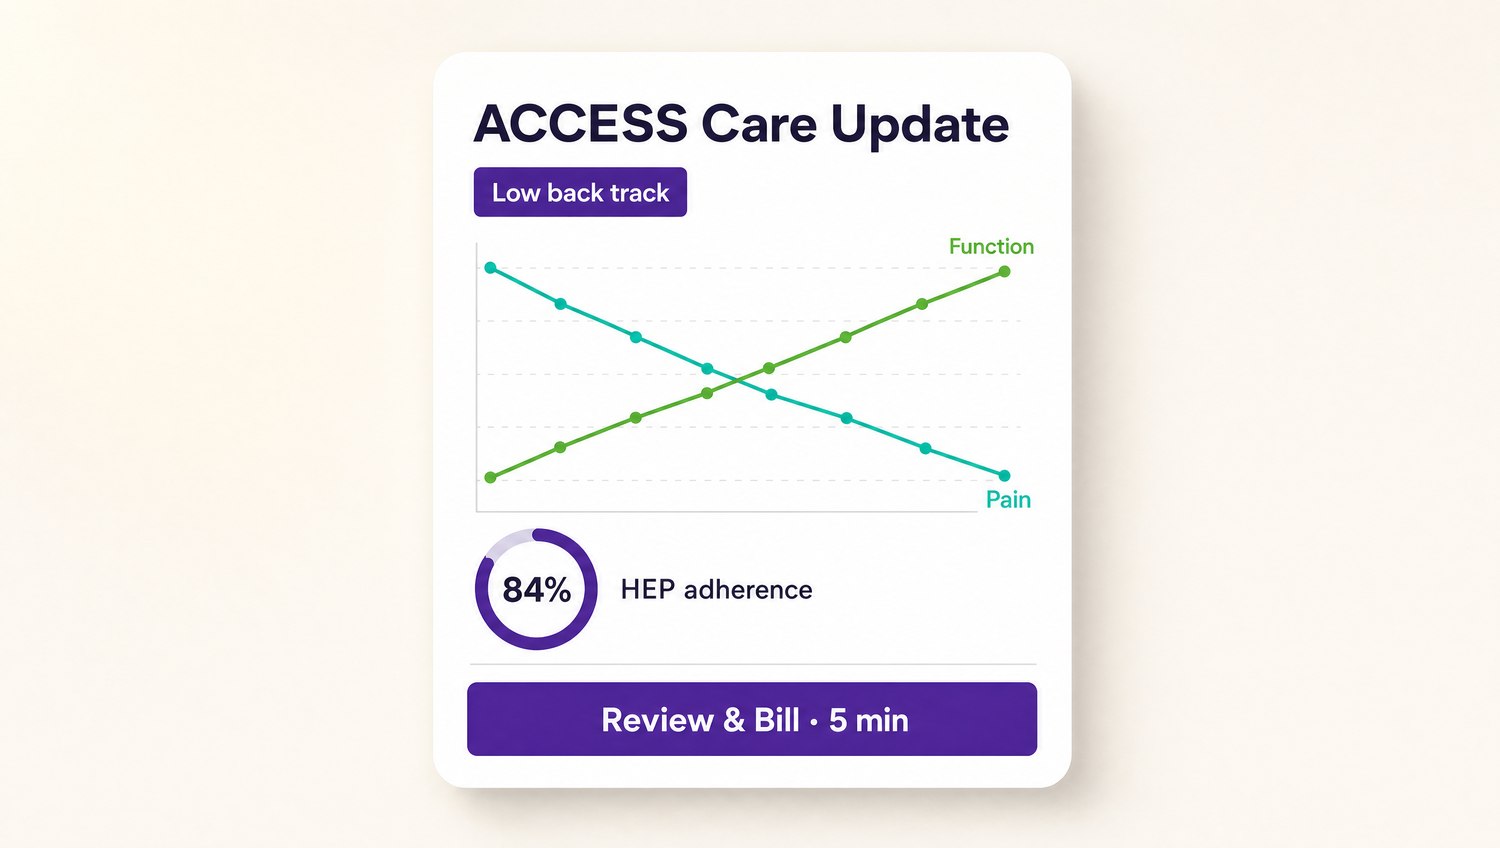
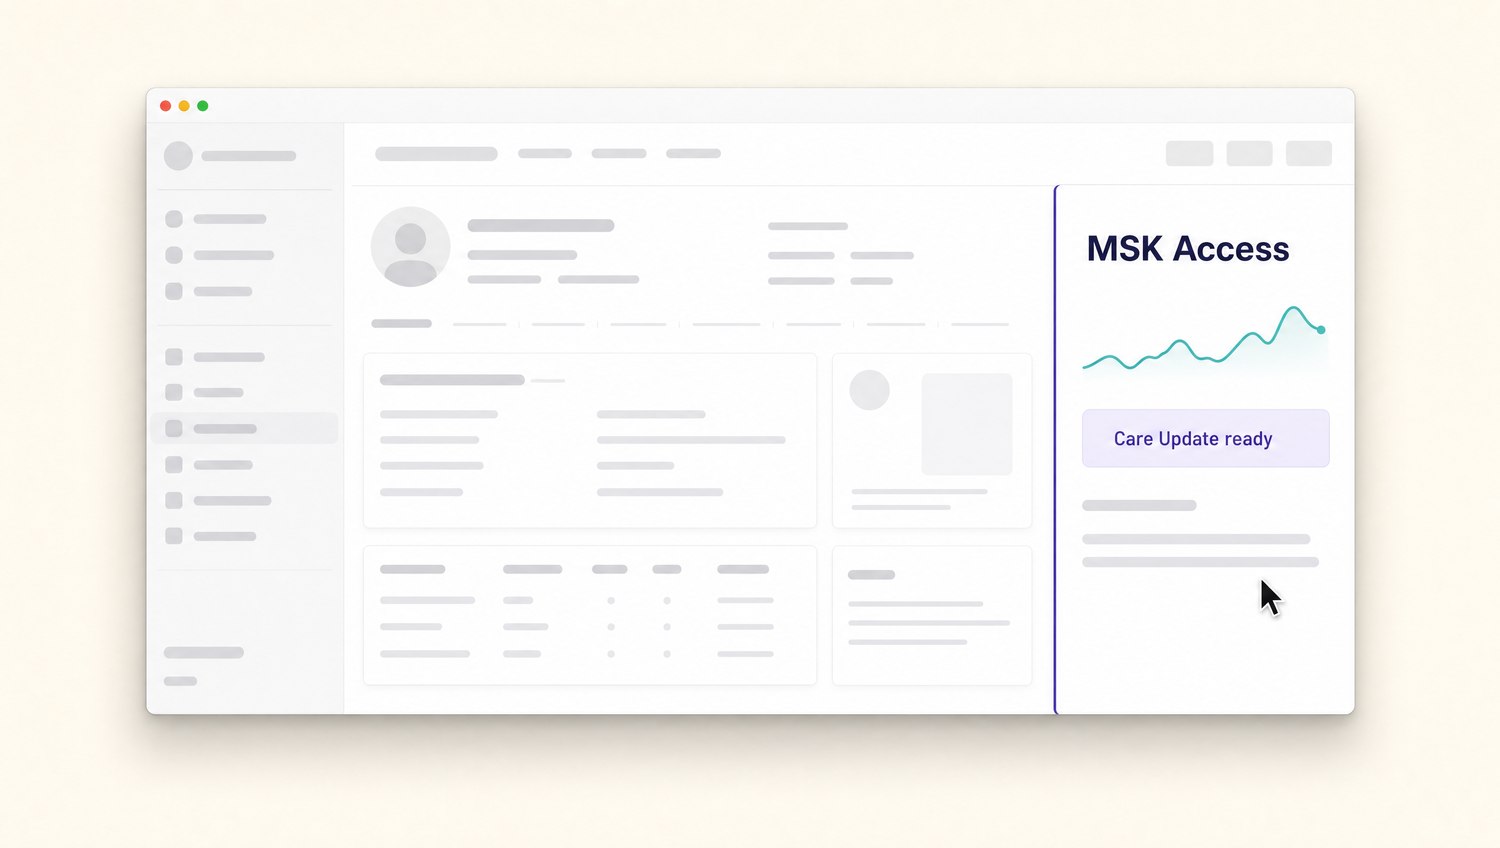
The Care Update arrives — PROM trends, exercise adherence, flagged escalations. Portal, pushed note, or embedded in your EHR.
Your clinician reviews and acts — about five minutes, one coordination activity, a real clinical decision.
The note goes in the chart — referencing the update, the track, and the action taken.
The claim goes out — track G-code, $30 per review, +$10 first review per track, up to 3×/year. $0 to the patient.
No new tab to remember. The Care Update panel embeds in the EHR, notes push into your existing workflow, and the platform preps the billing so the only thing your clinicians supply is judgment.
Co-management revenue scales with enrolled beneficiaries: up to $100 per beneficiary in year one, $90 ongoing per year, per MSK track — before a single additional visit.
Year-one figures, single track, per MSK Access proforma applying CMS ACCESS billing assumptions. Illustrative — every assumption in the calculator is adjustable.
Payers are watching the model's published outcomes. Prove the workflow on one site, and the same platform extends to your broader commercial population — capability by capability, mapped to your seat.

24/7 intake, triage, and booking. No login, no voicemail, no missed referral.
The visit documents itself — in person or virtual — and PROMs collect longitudinally without typing.
Panel-level PROM trends and CMS-published results — the evidence base for your next VBC contract.
Care navigators around surgery, monitoring between visits — recurring revenue on the relationship you keep.
Find the members who need MSK care before the ED does — payers are already signaling this model travels.
Medicare opened the door; the commercial market is lining up behind it. These payers have signed the pledge supporting outcome-aligned care — the panel you build under ACCESS is the panel this program expands into.
Payers that have signed the pledge, 2026. Names shown as text pending official brand assets; inclusion indicates pledge participation, not endorsement of MSK Access.
We ingest your roster or referral base, stand up the front door, and configure the review-and-bill workflow around the tools you already use. Weeks, not quarters.
